
- Back
- Back
- Back
- Back
- Back
- Back
- Back
- Back
- Back
- Back

Presented by Anastasia Chalkidou at ‘The Future of MedTech – Innovating for Tomorrow’, hosted by the British Healthcare Trades Association (BHTA) and AXREM on 13 May 2025 at The Mercure, Northampton.
Anastasia Chalkidou, Programme Director for Healthtech Guidance Delivery at NICE, delivered a clear message to delegates at this year’s BHTA and AXREM conference: medtech innovators now have more opportunities than ever to engage with NICE’s updated and more transparent evaluation processes.
Speaking during the second part of an engaging talk titled ‘Regulation in the Medtech Sphere’, Anastasia provided a high-level overview of the organisation’s transformation and its implications for the healthtech industry.
The first part of the talk was delivered by Dr Rob Reid, Deputy Director of Innovative Devices at the MHRA, which focused on the upcoming UK medtech regulations.
Over the past three years, NICE has undertaken a major transformation, which Anastasia explained is built on three core pillars: producing guidance that is more timely, more relevant, and has greater impact. For industry, this means a simplified and more accessible evaluation programme, with increased capacity and flexibility, and guidance that is better aligned with NHS system needs.
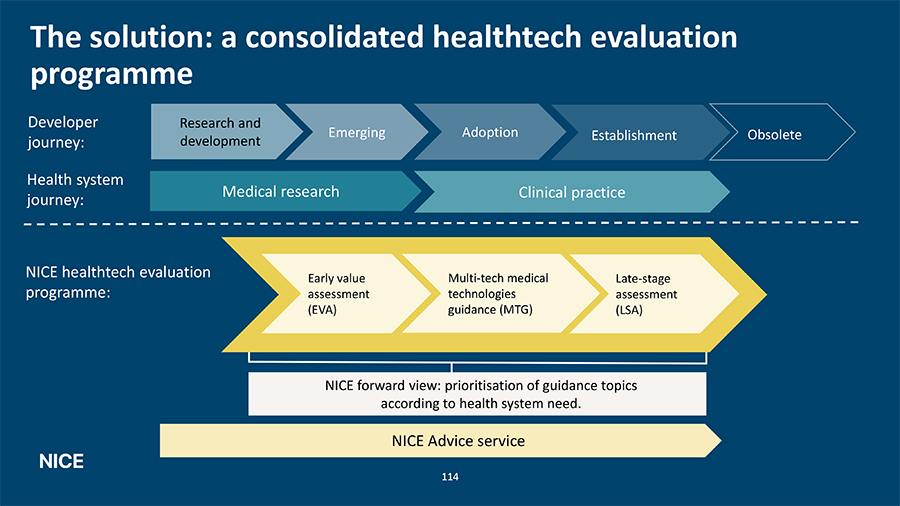
“We now have an early value assessment. That has become business as usual since last 12 months,” said Anastasia. This approach allows NICE to evaluate promising medtech, digital, AI, and diagnostic technologies sooner. These early assessments give conditional recommendations, provided there is a plan in place for further evidence generation, developed in partnership with stakeholders.
This marks a departure from the previous single technology evaluation model. With early value assessments, NICE is tackling the challenge of evaluating multiple products serving the same purpose. Now, NICE is able to make recommendations across groups of technologies, reflecting real-world usage and procurement within the NHS.
Another important development is NICE’s Prioritisation Board, which has now been operating for a year.
“It comes with a framework that explains in detail how we work on topic intel, the type of requirements that something needs to fulfil to be selected for evaluation with NICE,” explained Anastasia.
Decisions made by the board are publicly available and open to challenge, and NICE actively encourages input from clinicians and manufacturers to suggest technologies for evaluation as well as challenge certain decisions.
The HealthTech Evaluation Programme has seen notable growth. NICE’s digital health programme has also expanded significantly, with a threefold increase in evaluated products. NICE has also harmonised its processes with the publication of its unified healthtech manual, launched in March 2025, now moving into full implementation.
This harmonisation replaces fragmented and inconsistent evaluation methods with a single framework tailored to different types of technology. It promises more consistent timelines, enhanced support for evidence generation, and better alignment with wider NHS priorities. “It’s much easier now to access with fewer restrictions, greater capacity, and more flexible methods,” said Anastasia.
Beyond earlier and broader evaluations, NICE is piloting a late-stage assessment model. This focuses on high-spend, high-variation technologies already on the NHS procurement list, to determine whether pricing is justified and whether incremental innovation warrants broader adoption. This approach, said Anastasia, aims to ensure NICE “looks at incremental innovation and whether the price variation is justified”.
NICE’s transformation was shaped by early insights from the health system, which identified key needs: earlier signals of which technologies meet system priorities, more evaluations of digital solutions, and guidance on technologies already in market. NICE’s current programmes directly respond to these, providing earlier and more useful information for procurement, investment, and strategic decisions.
The message for industry is clear: whether a product is at the R&D stage or already in use, NICE now offers multiple routes for evaluation, conditional recommendation, and eventual system-wide adoption.
For BHTA members, NICE’s transformation presents a timely opportunity to engage with NICE earlier, more effectively, and with greater clarity on how products can achieve both recognition and adoption across the NHS.
See some of the slides from Anastasia’s presentation below:



At the recent British Healthcare Trades Association (BHTA) Conference 2024, Mark Chapman, Interim Director Medical Technology Digital & Diagnostics at the National Institute for Health and Care Excellence (NICE), delved into the NICE healthtech assessment lifecycle approach and innovative vs iterative healthcare products.
The BHTA Conference 2024 focused on the UK healthtech landscape over the next five years. It was a chance for BHTA members to hear from senior government and NHS speakers about how the changes made today will impact the future of the health service.
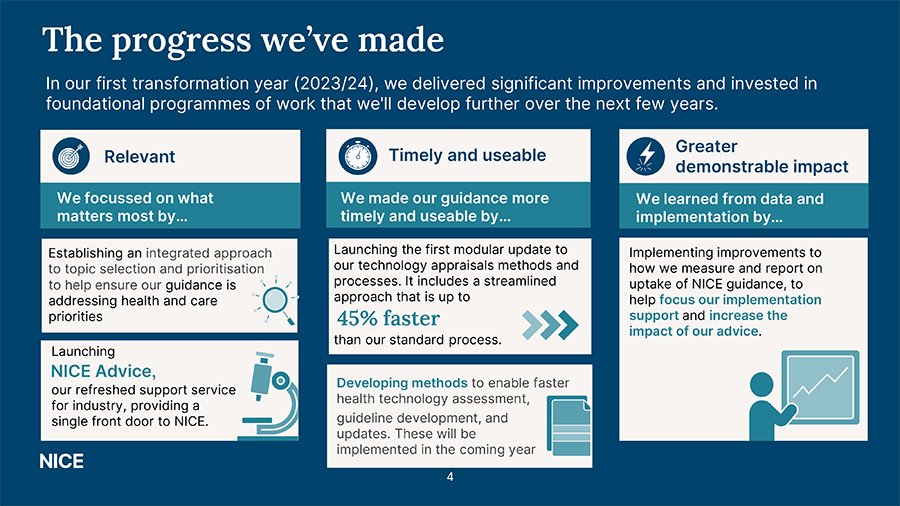
Mark began by explaining how NICE is transforming by developing guidance that is more:
Progress has been made on these changes, which are detailed on the slide below.
An important topic from Mark’s presentation was around whether products are innovative or iterative.
Mark said: “A product starts off massively transformative and innovative. Then, over time it iterates. By the end, it’s got a lot of additional items added to it. It’s the additional items that make it different to the predecessor, but you wouldn’t class it massively as innovative.
“The reason why it’s important to think about this is, for so many years, we’ve tried to polish what may just be another pair of shoes and convinced someone that they’re the better thing to have. That might be the case, but it’s not always the case.”
The MedTech Strategy touches on the right product for the right patient at the right time.
“When we think about innovation without differentiation, that’s what holds us back,” Mark explained. “Far too often, innovation has gone into the system, and the next innovation has come along. You don’t know whether the first one was the game-changer or the second one was the game-changer, because we’ve rarely done any full assessments.
“That’s what we want to shape NICE to be looking at more intentionally.”
With this in mind, NICE has introduced and refreshed its topic prioritisation programme. This allows NICE to select the right technologies for consideration of a NICE assessment, dependent on the evidence, availability, the access to it, and the need in the health and social care system.
Then, through various stages, NICE will start looking at how much this would cost, the system impact for that investment, population impact for that investment, and these may be cost saving. Whereas historically in the healthtech programme, everything was forced into proving cost saving.
“Once a product has been selected, we’ll embark upon a health technology assessment,” continued Mark. “A health technology assessment is a collective term that describes a set of methods and approaches to assess the value proposition of a technology.”
A key point from Mark’s presentation was around NICE’s life cycle approach to healthtech assessments. See the slide below for further details.

Where possible, real-world evidence (RWE) will be prioritised for late-stage healthtech assessments, added Mark.